Differential Diagnosis
Caveat: Although the differential diagnosis for cavitary lung lesions is quite broad, based on the morphologic appearance of this lesion and the clinical presentation, the only considerations in this particular case would include infection and neoplasia.
Infection
- Mycobacterium tuberculosis
- Bacterial lung abscess
- Anaerobes; mixed anaerobic-aerobic infection
- S. aureus
- S. pneumoniae
- K. pneumoniae
- Pneumocystis jiroveci pneumonia
- Various fungal and atypical bacterial infections
- Septic Emboli
Neoplasia
- Primary bronchogenic carcinoma
- Squamous cell carcinoma
- Adenocarcinoma
- Metastases (e.g., squamous cell)
- Lymphoma
Autoimmune
- Wegener granulomatosis
- Necrobiotic nodules of rheumatoid disease
Emphysematous bullae / bullitis
Post-traumatic laceration or pneumatocele
Bronchiectasis
Pulmonary infarction
Sarcoidosis (rare)
Congenital lesions
- Pulmonary sequestration
- Cystic adenomatoid malformation
- Bronchogenic cyst
Discussion
Background
Adenocarcinoma is the most common histologic cell type of primary bronchogenic carcinoma. Whereas all of the various histologic cell types of non-small cell and small cell lung cancer are associated with cigarette smoking to some degree, adenocarcinoma has the weakest association. Most primary adenocarcinomas of the lung are located peripherally or juxtapleural in the upper lobes. Up to one-third of primary adenocarcinomas of the lung may occur in a more central location. Although squamous cell cancer is the cell type most often characterized by cavitation, adenocarcinoma is the second most likely cell type to cavitate. Various lung infections and lung abscesses including tuberculosis can also be characterized by cavitation. A helpful radiologic observation that can be used to steer the differential diagnosis is the wall thickness of the lung cavity. As a general “rule of thumb” the more irregular and the more thickened the wall of the cavity, the more likely the lesion is neoplastic.
Clinical Findings
Primary lung cancer generally presents in the 6th-7th decade, although the range of presentation is quite broad. Adenocarcinoma is the most common cell type manifesting in both women and nonsmokers. Over 90% of patients with lung cancer are symptomatic at presentation. Large masses may produce cough, dyspnea, and/or chest discomfort. Pleural and chest wall invasion results in pleuritic or localized chest pain. Central adenocarcinomas may produce symptoms of bronchial obstruction. Paraneoplastic syndromes such as thrombophlebitis and non-bacterial thrombotic endocarditis may also occur in association with lung adenocarcinoma. A minority of patients are asymptomatic and diagnosed incidentally because of abnormal chest radiography acquired for unrelated reasons.
Pathology
Gross
- Peripheral, juxtapleural mass; frequent central fibrosis; pleural puckering; spiculated borders.
- Isolated peripheral mass (50%); peripheral mass with lymphadenopathy; central mass (50%).
- Variable size; small nodule-to-large mass occupying the vast majority of the affected hemithorax.
- Contiguous pleural invasion; progression to circumferential pleural involvement similar to that of diffuse mesothelioma.
Microscopic
- Glandular differentiation; mucin production.
- Acinar; papillary; bronchioloalveolar; and solid growth patterns.
- Histologic heterogeneity; coexistence of several growth patterns in a single lesion.
Imaging Findings
Radiography
- Solitary nodule or mass with variable border morphologies and characteristics
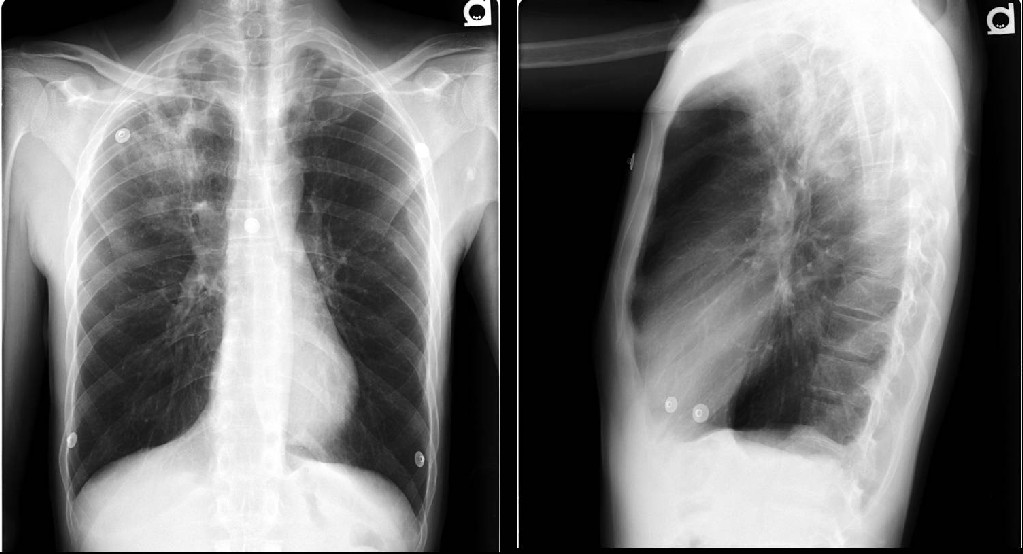
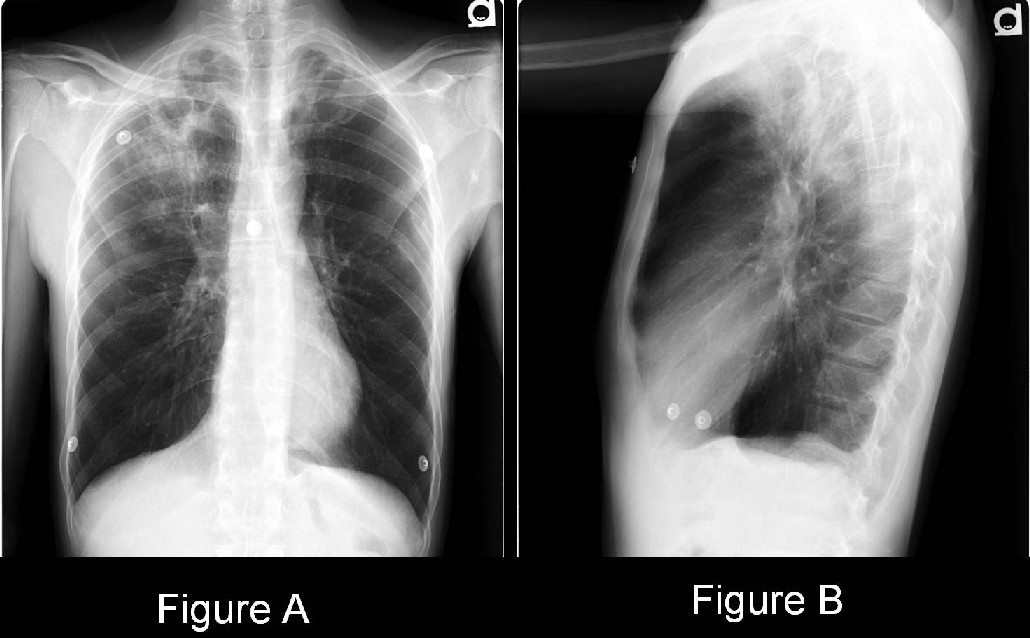
- Ill-defined (Fig. A)
- Well-defined
- Lobulated (Fig. A)
- Spiculated
- Mass may cavitate (Fig. A)
- Associated hilar/mediastinal lymphadenopathy
CT
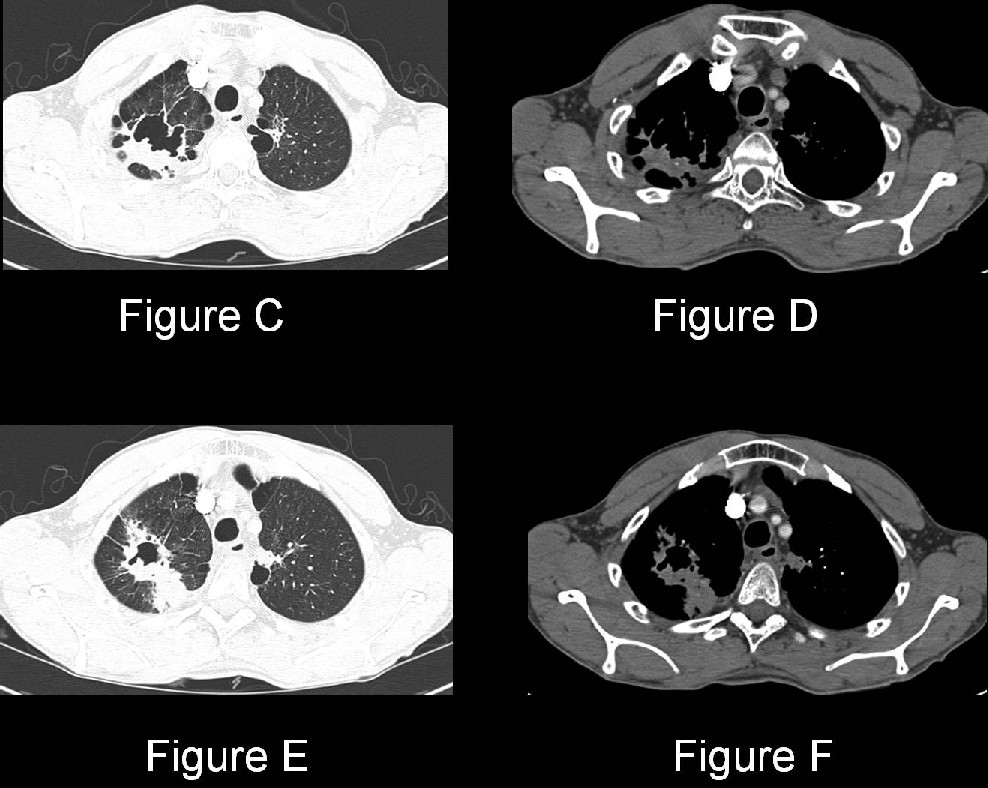
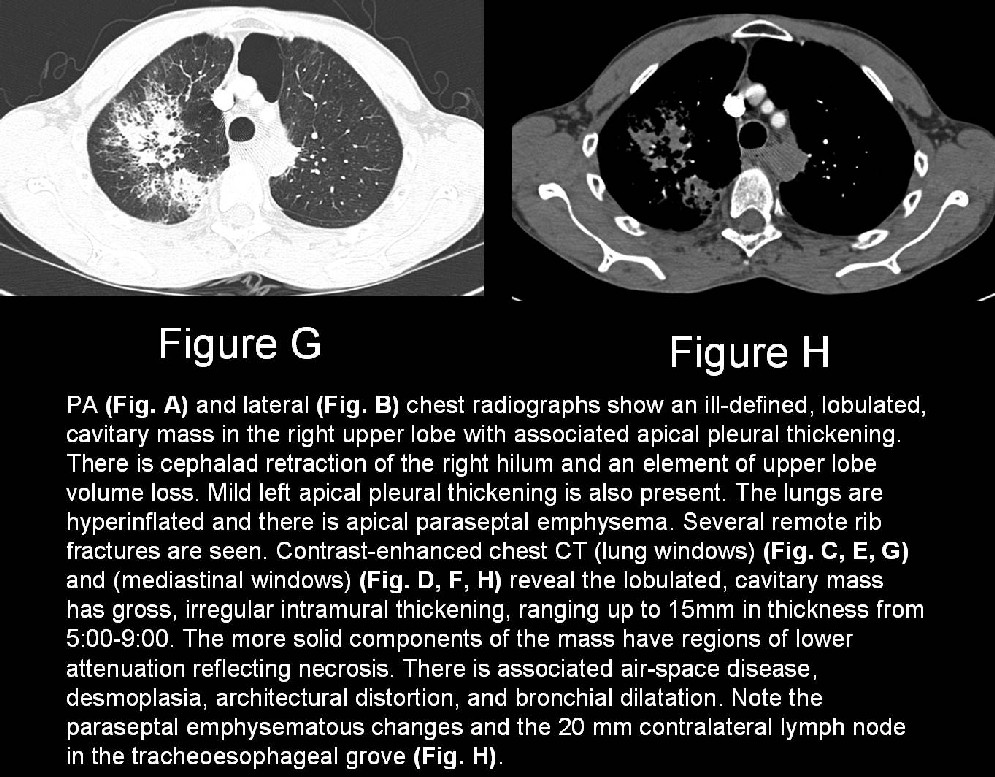
- Peripheral nodule or mass with lobulated or spiculated borders (Fig. C-H).
- Mass may cavitate (Fig. C-H).
- Eccentric calcification(s) may be identified; more common in larger lesions.
- Varying degrees of enhancement following iodinated contrast media administration.
- Pleural effusion; pleural implants; or both in cases of neoplastic pleural involvement
- Osseous destruction in cases of chest wall involvement
MRI
- More sensitive for demonstration of chest wall invasion
- Useful alternative to evaluation of mediastinal and hilar involvement on patients with contraindication to receiving iodinated contrast media
PET
- High sensitivity and negative predictive value in lesions > 1.0 cm diameter
- Useful adjunct to staging patients for unsuspected lymph node involvement and extrathoracic disease
Treatment and Prognosis
Management options and patient outcome and survival depend greatly upon the stage of disease at the time of clinical and/or radiologic presentation. Treatment may include resection, lymph node dissection, radiation, and chemotherapy.
Caveats
- Lung cancer is also associated with exposure to various occupational and environmental agents such as asbestos and radon.
- Conditions characterized by pulmonary fibrosis (e.g., Usual Interstitial Pneumonia (UIP); Progressive Systemic Sclerosis (PSS)) are associated with an increased incidence of lung cancer, adenocarcinoma in particular. These latter cases more often present with lower lobe lung cancers.
- Whereas irregular spiculated lesion borders are suggestive of neoplasia; they may also be seen in benign lesions. Furthermore, lung cancer can also manifest as a well-defined, non-lobular nodule or mass.
- Additional morphologic findings suggestive of neoplasia include: eccentric or irregular intramural nodularity or thickening; nodular inner margins, notched outer margin, associated soft tissue mass, and lymphadenopathy.
Suggested Readings
- Collins J, Stern EJ. Chest Radiology, The Essentials, Second Ed. Philadelphia, PA: Lippincott Williams & Wilkins. 2008, p. 110-112, 164-193, 243-246.
- Honda O, Tsubamoto M, Inoue A, Johkoh T, Tomiyama N, Hamada S, Mihara N, Sumikawa H, Natsag J, Nakamura H. Pulmonary cavitary nodules on computed tomography: differentiation of malignancy and benignancy. Journal of Computer Assisted Tomography 2007; 31(6):943-949.
- Hours S, Nunes H, Kambouchner M, Uzunhan Y, Brauner MW, Valeyre D, Brillet PY. Pulmonary cavitary sarcoidosis: clinico-radiologic characteristics and natural history of a rare form of sarcoidosis. Medicine (Baltimore) 2008; 87(3):142-151.
- Parker MS, Rosado-de-Christenson ML, Abbott GF. Lung Cancer: Adenocarcinoma. In: Teaching Atlas of Chest Imaging. New York, NY: Thieme Medical Publishers, Inc. 2006, p. 291-295.
- Vourtsi A, Gouliamos A, Moulopoulos L, Papacharalampous X, Chatjiioannou A, Kehagias D, Lamki N. CT appearance of solitary and multiple cystic and cavitary lung lesions. Eur Radiol. 2001; 11(4):612-622.
Original case written by its authors at Virginia Commonwealth University and published at this address as part of a weekly teaching collection. Reproduced here as an archive.